Ever heard of grand mal seizures? It's the type of seizures most think about as seizures, with unconsciousness and violent jerking movements.
I'm in clinic today. On her history form she has written "mini mall seizures".
I usually shop at mini-malls, but I think she means petit-mal seizures. These are also known as absence seizures and not associated with jerking motions.
Friday, July 27, 2007


Monday, July 16, 2007
Poor historian
I'm in clinic again... the bane of the non-pain anesthesiologist. A 60-some year old woman is here for surgery. She's had a history of heart failure. (Her heart is damaged so it doesn't pump very efficiently) She's a terrible historian.
Now for non-medical types, this doesn't mean she didn't know that Washington crossed the Delaware. It means that she's a terrible reporter of her own medical history. For different patients it means different things. To some it means that they can't remember what they've had done in the past or what medical conditions they have. To others it means that they ramble on so much it's hard to separate the medical information from random stories about their puppy. And my favorite group is the group where they're so vague about things that it takes 14 follow-up questions to get what you want from them.
"So how bad has your heart failure been" (Looking at the chart with 6 heart failure meds on.)
"Oh I don't really have heart failure"
"Hmm... really. Can you climb a flight of stairs?" (I don't care if she has stairs in her house, I just want to know if she can tolerate minor exercise)
"Oh I don't really climb stairs with my back and all" (Meaning she can't do it)
"How about walking, how far can you walk?" (Easier than stairs)
"Oh not far..."
"Do you ever get chest pain or shortness of breath?"
"Well not really.... well only if I walk too far." (Meaning yes all the time)
(inside) *sigh*
So I look again through the notes. There's a note from the Primary care provider (PCP) "Will stress before surgery." Now someone there has a good idea. Good to know if this lack of function is due to her heart or her back before we possibly kill her in the operating room.
I flip to the studies. I see a non-stress echocardiogram (essentially a heart ultrasound picture) from five months ago showing diastolic dysfunction. And a stress echocardiogram (same pictures, but while giving a chemical to stress the heart) from last month. "Indeterminate. Study cancelled due to hypertensive response." So they cancelled the stress in the middle because her blood pressure got too high. Fine. What did they do about that. I see another non-stress echocardiogram from two weeks ago. Hmm.... curious. So the stress was unable to be done, so they repeated a test that DIDN'T stress the heart, and had results we ALREADY knew about.
So it's six days til her surgery, I have a patient with known heart failure, maybe shortness of breath, maybe chest pain, two non-stress tests, and an indeterminate stress test. Someone also has decided before me that a stress would be a good idea, but never really followed through. So I have six days (including two weekend days) to get her stressed (a different type of stress test) or cancel the surgery. Luckily the ladies out front (the wonderful office staff) are able to get her scheduled for early next week. I cross my fingers and let her go.
The intern asks me what happens if the stress is positive next week. Good question. If it's negative, then I'm just a worry-wort and paranoid about nothing but she should get her back fixed. If not, then they need to evaluate her to see if anything can be done to optimize her heart before her elective surgery. This may mean changing her medications, or performing a heart catheterization, or more.
Did I tell you I love clinic?
Monday, July 02, 2007
Study Says Chatty Doctors Forget Patients
Study Says Chatty Doctors Forget Patients
Funny... except for the patients. Published in the Archives of Internal Medicine via the New York Times
Funny... except for the patients. Published in the Archives of Internal Medicine via the New York Times
Sunday, July 01, 2007
Playing Doctor
I got to play "real" doctor this weekend.
Not that an anesthesiologist isn't a real doctor, but it's not immediately what comes to mind when you say doctor.
My friend volunteers at a free county medical clinic run by medical students some weekends. The medical students see patients and are staffed by physicians from the community. They were running short of physicians this week so I offered my services.
It was a little different than my usual Saturday morning, but a little fun nonetheless. I only had to ask a few questions to the "real" doctors.
A lot of me saying to medical students "just warning you... I'm an anesthesiologist."
Thursday, June 14, 2007
Staffing shortage
This week we opened a new building... brand new operating rooms, new offices, etc. beautiful place. Still some growing pains as we are somewhat short staffed.
Yesterday, we had an urgent case to start. No residents or CRNAs were available since it was a lecture day and the available people were giving breaks so other people could go to their lectures.
Anyway they had an available OR, and I myself was giving lunch breaks....
So I just went ahead a did the case myself.
I know this doesn't sound too strange to most of you. It's probably the norm in most places. But being at an academic institution I haven't done a case by myself, well ever. In the few years I've been staffing, I always work with a resident or CRNA. Before then I was a resident so I worked with a faculty member supervising me.
It's nice knowing you have your stuff together well enough that you can do a case by yourself at a moments notice.
Yay me.
Tuesday, June 12, 2007
Preop Hijinks
So I'm in clinic today and I'm talking to a patient about his health problems for some surgery or another. All of a sudden he stands up, unbuckles his belt buckle, unzips his pants and starts tucking his shirt in.
Now I've done this before too, but usually it's in my bedroom before I go to work or if I'm in the bathroom or if I'm alone somewhere with no hope of someone walking in.
Weird and unsettling.
I just acted like nothing was happening and averted my gaze.
Now I've done this before too, but usually it's in my bedroom before I go to work or if I'm in the bathroom or if I'm alone somewhere with no hope of someone walking in.
Weird and unsettling.
I just acted like nothing was happening and averted my gaze.
Wednesday, June 06, 2007
Condolences
As you no doubt have heard by now. A plane with an organ transplant team crashed into Lake Michigan on Monday. All six aboard were lost.
Condolences to the families of the two doctors, two organ donation specialists, and two pilots.
They perished in the quest to save the life of another.
Condolences to the families of the two doctors, two organ donation specialists, and two pilots.
They perished in the quest to save the life of another.
Monday, June 04, 2007
Tragedy
I don't really want to talk about it now but do me a favor.
Go home, kiss your wife or husband, boyfriend or girlfriend, hug your children.
You never know when it's the last time.
More later... maybe
Go home, kiss your wife or husband, boyfriend or girlfriend, hug your children.
You never know when it's the last time.
More later... maybe
Saturday, June 02, 2007
Tuberculosis
Everyone knows the name of Andrew Speaker. If you don't he's the person carrying the multidrug resistant tuberculosis(TB) stain all over the world.
First, Tuberculosis. It's a difficult disease to treat... months of antibiotics are required in most instances, and usually more than one type of antibiotic. Because people generally feel fine when they have this diagnosis they often quit taking the medication. This leads to more drug resistance.
I find a few things very funny about the case.
1. He's a personal injury lawyer. If someone else had done this I bet he'd be on TV advertising for people to call him to get their "rightful settlement"
2. His new father-in-law... works for the Centers for Disease Control. Speciality -- tuberculosis. You can't make this stuff up.
3. His name came up when he crossed the border from Canada. "including instructions to hold the traveler, don a protective mask in dealing with him, and telephone health authorities." The border inspector ignored these warnings because they appeared discretionary and the man appeared healthy. Good to know the system works. Good thing he's wasn't a terrorist. I imagine if he had been of middle eastern ethnicity he would have been face down handcuffed in a ditch in twelve seconds.
I'll give the guy some credit. He's probably not extremely infective from what I know about TB. He wasn't coughing, he probably didn't have an acute infection. He also picked it up somewhere long ago. And it was just recently found on an xray for something unrelated.
But also some problems.
1. He states he didn't know the risk of what he was doing, but when he was told not to come home he went to extreme pains to get home. He flew from Atlanta to Greece for his wedding, warned not to travel. Then flew to Rome, Italy. Warned again not travel. Then got to Prague, Hungary flew to Montreal, Canada then drove across the border to avoid authorities. Sounds like someone deliberately trying to skirt the system.
2. I'd hate to miss my wedding and honeymoon. But questions are now arising to whether a wedding took place. One article states "There was no wedding. They came for a marriage but they did not have the required papers." Good planning on his part. If I was the prospective bride I'd be pissed off.
Thursday, May 31, 2007
Keywords
So I've realized for the last few posts that you can add keywords to each post and people can read those posts with those keywords only.
I'm anal enough that I'm going back and adding keywords to all my old posts. Hope this makes reading more enjoyable.
(I'm assuming people are reading)
I'm anal enough that I'm going back and adding keywords to all my old posts. Hope this makes reading more enjoyable.
(I'm assuming people are reading)
Wednesday, May 30, 2007
Random walls

I'm walking out of work late yesterday. I'm tired. I'm on cardiac call i've been here for 12 hours. Not bad hour-wise but i've had to work with one of the stressful surgeons and just finished helping code a patient in the operating room.
I just want to go home and put up my feet...
All of a sudden there's a wall along the corridor where I usually walk out. It was open this morning
"Detour -->" I guess they're finally connecting the new building to the old one.
Now I wander through the basement and finally get to my car.
Perfect ending to a long day. Hope I don't get called back in.
Friday, May 11, 2007
Yay!
I got a page from a friend today saying oral board results were posted.
I passed!
It's about a week and half earlier then they said scores would be up, but I'm glad.
Relief.
I passed!
It's about a week and half earlier then they said scores would be up, but I'm glad.
Relief.
Tuesday, April 24, 2007
Oral Boards - Done
I've been back from DC. Oral boards are done.
Yay!
Topics were anticipated. Did I study enough, hard to say... would studying more been more helpful... doubtful.
I think I did okay... but who knows for sure. I'll find out at the end of May.
At least it's over, for now.
Yay!
Topics were anticipated. Did I study enough, hard to say... would studying more been more helpful... doubtful.
I think I did okay... but who knows for sure. I'll find out at the end of May.
At least it's over, for now.
Monday, April 23, 2007
Transvaginal Cholecystecytomy
In a word -- Yuk!
These words together mean removal of the gallbladder through the vagina.
Yuk yuk yuk.
If I had a vagina, you're not removing my gallbladder through it.
And to boot there's a Natural Orifice Surgery Consortium for Assessment and Research.
You can leave my natural orifices alone... I mean look what great scientific advances there are in this decade.
New York Times online via Book of Joe
Monday, April 16, 2007
DC in the spring
Ah to be in Washington DC in the spring.

Blossoms on the trees.
Spring is in the air...
NO!
I'm in DC for anesthesia oral board exams
Its 40 degrees outside.
There's a wind advisory...
The plane was shaking like a laundry dryer as we were landing... and I swear we were going sideways for several seconds.
AND I'm taking oral boards tomorrow.
I'm a little stressed
I'm back to the books for last minute cramming... maybe a short nap.
More later.
Monday, March 12, 2007
Drug interactions
A friend called and asked me: "Are there any drug interactions between Darvocet and albuterol?" Her friend had just had surgery and was on pain killers (Darvocet - acetominophen/proproxyphene) and wanted to take a puff on her inhaler (Ventolin- albuterol).
I said I didn't think so. The narcotic has lots of interations, but not likely with albuterol. "Why?" I asked.
"Well she saw this Law and Order where this girl poisoned her mom with darvocet and albuterol."
Hmm... Law and order? "You sure that wasn't darvocet and ALCOHol not ALBUTERol?"
"Hmm... yeah probably, see ya bye!"
I guess it's all in the details.
Monday, February 26, 2007
Clinic
Been in clinic a lot the last few weeks. Almost half my work time. By now i'm almost suicidal... I didn't go into anesthesia to do so much clinic
(no offense to those who are actually suicidal)
(no offense to those who are actually suicidal)
Sunday, January 14, 2007
Room temperature
It's important to keep the patient in warm in most cases. Most cardiac cases this is not an issue much because the heart-lung bypass machine has a heat exchanger on it which allows the perfusionist to warm or cool the (patient's) blood as it goes through it.
We were doing a big cardiac case under left heart bypass -- where part of the blood is taken after it gets passed through the lungs, and rerouted to the femoral artery in the groin so that work can be done to the descending aorta with most of the blood flow being perserved. This is nice so that damage to important organs like the kidneys and intestines can be limited.
Since we have less control over temperature because it's only partial bypass, we had the room temperature way up. It was warm for me, but must have been killer for the surgeons who were wearing waterproof gowns, etc.
On of the attending surgeons was scrubbed in and asked for temperature to be turned down. He's generally very expressive. "Turn down the temperature or I'll vomit in the wound and the patient will get septic and die!" I just about died laughing...
(For those not in the know... sepsis in a severe systemic infection caused by bacteria. If you vomited into a patient surely this would happen but it's not a scenario you contemplate ... well ever.)
Tuesday, December 05, 2006
Working too hard?
Imagine my suprise to get my schedule this month to find that I have 3 random vacation days this week. Apparently I'm not using my vacation fast enough. I got some Christmas shopping done, and put up some decorations.
Brr.
Brr.
Wednesday, November 22, 2006
Sexily dressed doctors may be dangerous
My resident in clinic showed me this article today from the ABC news web site
Sexily dressed doctors may be dangerous
First of all, it must be a slow news day. Second of all the first paragraph mentions Grey's anatomy. And we know that all hospitals are like the hospitals on TV.
Sad.
Sexily dressed doctors may be dangerous
First of all, it must be a slow news day. Second of all the first paragraph mentions Grey's anatomy. And we know that all hospitals are like the hospitals on TV.
Sad.
Wednesday, November 08, 2006
A day
Been gone for a while, busy at work, vacation (wasted nothing too fun), then busy at work sorry there's been not much posting.
Put in a LVAD (left ventricular assist device) in a patient, which is an assist device to help the left side of the heart. Another patient had an RVAD which was a device to help the right side of the heart which we took out. Stressful day though... now doing some general cases while the overnight guy does a heart... what a way to make a living.
Put in a LVAD (left ventricular assist device) in a patient, which is an assist device to help the left side of the heart. Another patient had an RVAD which was a device to help the right side of the heart which we took out. Stressful day though... now doing some general cases while the overnight guy does a heart... what a way to make a living.
Monday, September 04, 2006
high glucose
my fasting glucose this am was high, 167 usually it's been running high but only in the one-teens to 120s 3 confounding factors.
1)I was up all night teeing up a heart transplant
2)I'm using a different glucometer, the one at work, rather than my usual at home
3)I had Chinese takeout for dinner.
Sadly i suspect It's number three.
1)I was up all night teeing up a heart transplant
2)I'm using a different glucometer, the one at work, rather than my usual at home
3)I had Chinese takeout for dinner.
Sadly i suspect It's number three.
Wednesday, August 30, 2006
Being a patient
So apparently I have diabetes. I went innocently enough to the doctor's office to ask about getting a sleep study for sleep apnea (which I probably have). So he's asking all these questions and running all these tests because it's the first time I've gone to the doctor's in years. My Hemoglobin A1c was through the roof. The hemoglobin A1c measures the average blood sugar over the last 120 days or so in your blood. Also I had a pretty high blood pressure in the office.
Now I'm checking my glucose (almost) every morning, supposed to be checking my blood pressure regularly so he can decide if I need an anti-hypertensive medication. My sleep study is scheduled, and I'm making calls to the insurance company to see if things are covered.
I guess I'm a set up for this. Even though I'm in my early 30s, I'm overweight, I eat poorly, diabetes and hypertension run in the family ... let me continue.
I don't think I'll like being a patient.
Sunday, August 13, 2006
Black Cloud
(Sorry that postings have been so sparse. I'll fit in more time)
Some say that I have a black cloud. They're wrong. I have a storm cloud following me.
Let me clarify. In the medical profession, (I don't know if this concept exists in other fields) if you attract all the worst, bad, complicated cases, or when you're on call everyone and their mother has to come to the hospital, then you have a black cloud. It's possible to have a white cloud. And sometimes the white cloud cancels out the black cloud.
Anyway, I think the origin of my black cloud was my first day of residency. To sum it up... out of the 2 patients I took care of that day, half of them did not live to see the next day. Not that I was responsible, but it was still traumatic nonetheless. I had patients die the first two times I was on call as an attending physician.
Friday night, this continued. When I came in during the afternoon, here's a partial list of what was left to start -- 3 liver transplants, a heart transplant, and 2 endovascular thoracoabdomical aortic aneurysm repairs in addition to a myriad of other smaller cases. Also on the table was a facial reconstruction that had been going 8 hours so far, an open thoracoabominal aortic aneurysm repair, and liver resection that had lost six liters of blood.
Needless to say I was up all night. Two liver transplants had been finished (I was not responsible for this) the heart transplant also (not me as well, yay) The thoracoabdominal aneurysm finished after 15 hours of work, the facial reconstruction had been going 24 hours with no end in sight, and another ENT reconstruction case had not only finished, but had gone back to the OR 3 times in addition because things didn't look well. At least I was working with good residents and colleagues. It makes things a bit more manageable.
Saturday, July 08, 2006
TEE?
Sorry it's been a while. I've been on vacation for three weeks... but it's not really a vacation because I've been studying for anesthesia boards (third time around.. yikes, wish me luck)
Anyway I was watching Discovery Health (flipping past really... I rarely WATCH it) and there was a cardiologist talking about a test they "rarely" do in the ER. A TEE. A TEE stands for TransEsophageal Echocardiogram. Break it down -- basically a picture of the heart using soundwaves with the probe being in the esophagus (your feeding tube) Then they have the patient talking about it and him being scared and they show a picture of a medical instrument and you're supposed to assume it's a TEE.
BUT IT'S NOT!!!
They show what is probably a gastroscope -- a camera used to see into your stomach. And I can guess why they used that instead. It's kinda like a TEE, almost the same shape, put down the same tube, but more melodramatic because it's got a light at the end of it and they pointed the light into the camera and it faded out to the next scene and ooooh.... aaaaahhhh....
Anyway NOT the same
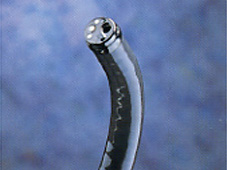 |  |
| Tip of gastroscope probe | Tip of TEE probe |
| Images used without permission fromFujinon Singapore and St. Michaels Hospital respectively | |
Monday, June 12, 2006
Sixteen Kids?
Just got done watching a bit(most) of a show on Discovery Health called "On the road with 16 children." It's about a family vacation of a family with 16 children.... that's a lot of kids! It's interesting, but I'm uncertain of why it's on the "Health" channel.
Tuesday, June 06, 2006
Can't sleep
Ugh. I'm on overnight call in the hospital. As staff it's only about once an month or so... which I can't complain about. What I can complain about is how it screws up my sleep schedule. All the cases finished about an hour ago (Ugh... so much neuro) and now I have the oppurtunity to sleep and of course I am taking advantage of this by being -- completely awake! By the time I'm sleepy, I'll either be paged to start some non-emergent "emergency" case, or it'll be time to go home where I have to sleep on my own time. Yuk. Whatever... my sleep hygiene is horrible anyway.
Wednesday, May 31, 2006
Memorial day weekend
Of course I was on call memorial day weekend. Luckily because it was a long weekend and they split up the call between two people so I had to endure a mere 48 hours on call.
For the first part of it, I worked a full day on Friday... an old lady with three valves that needed to be replaced. Uncharacteristically I got to leave at a reasonable hour... There had been rumors abound about a case to go Saturday morning... in fact I had first heard about "the emergent case for Saturday" on Thursday... so i waited all day on Friday for the surgeons to book it so I could plan my day better for Saturday. All day long... no case booked... everyone from the surgeon's secretary to the surgical PA to the perfusionist had heard that the case was going Saturday "for sure" Still it hadn't been booked by the time I left. I guessed they would page me when it was booked so I could set my alarm etc... imagine my surprise when I woke up Sat morning to no pages. Yipee...
I got about halfway through the day and then decided I would go grocery shopping and buy some food to grill out... steaks, pasta salad, corn, the works... no sooner than I get home from the store. [beepity beep beep] I call the OR front desk. "Type A dissection to arrive at the hosiptal in 30 minutes, Dr. *namedeleted* wanted everyone in" Fine. A Type A dissection is a tear in the first part of the aorta after it leaves the heart. This is an emergency because in that portion of the aorta is the blood vessels that supply the heart itself, and the beginnings of the blood vessels to the head. If this rips further then the heart or brain (respectively) will have no blood supply. Steaks in the fridge... hop in the car. I get the the hospital... perfusion is there, the cardiac nurses are getting there. "Where's the patient?" asks the perfusionist, "Lets get the show on the road" I don't know I think they're being flown in. Okay. Quick call. "They say they're not flying anyone in, but I could be another helicopter service". I find out that the ER doesnt know about the patient, the cardiothoracic resident if fact is at home on the couch because he hadn't heard, and no one knows about the patient. Yikes...
So we're sitting around for 45 minutes waiting for the word, when the surgeon calls in to the room. "She's in the ER, we need to go now". I grab the resident and we head downstairs, I find a woman in her late 20s, slightly tearful. I go through my history with her quickly and explain what's going to happen, she's no longer slightly tearful, but very tearful now. I reassure her and we start wheeling her back.
*time warp*
12 hours later it's 6am and we've just finished her operation. Lots of bleeding, but she's doing fine, I'm exhausted from being up all night. Luckily I get to go home, the resident needs to start an "emergency LVAD that we heard about 2 days ago" Hopefully his staff will let him out for a nap.
I know I need one
Tuesday, May 23, 2006
death in the or
Somehow as morbidly ill someone is when you are in charge of their case, as little chance as they had of surviving.... you can't help but take it a little personal when they expire in the OR.
More later... maybe.
More later... maybe.
Wednesday, April 26, 2006
Administrative Professional's day
So today is Secretary's day... I mean administrative professionals day so I decided to go pick up some pastries and bagels at Panera for the office staff. Amazing how far $40 bucks worth of carbohydrates gets ya. Anyway, I went there last night and gave them my last name. This morning I went in and asked to pick up my order... "Here you are Dr. [name omitted]" Now I don't remember telling them I was a doctor. Usually I look pretty scrubby in the morning... today I had a shirt and tie on because of clinic. Maybe I look doctorly? maybe the only people ordering large amounts of pastries are doctors? anyway. weird.
Thursday, April 13, 2006
ugh... clinic
so you see. i'm an anesthesiologist. and I'm wearing a tie. how awful.
no really I don't mind that much, but I never expected to wearing a tie much in anesthiology... maybe a tie made out of scrub material (Hmm that might be funny)
anyway. i'm in pre-op anesthesia clinic. surgeons send us patients so we won't cancel them the day of surgery... so we look at the problems they've overlooked in favor of the surgical repair and we make sure they have nothing that will kill them.(oversimplification... sorry)
anyway for some strange reason the phone has been ringing off the hook today. Really it NEVER rings. Today it's so-and-so from Oto "Have you seen Mr. X yet?" or whoever from Urology "Does Mrs. Y need to come down and see you?"
Argh... I'm busy surfing the net. And seeing the five other patients you just sent down here.
I'll just let resident see them all... it's lunchtime isn't it?
Friday, March 10, 2006
Awareness followup
Sorry I haven't posted in a while, I've been busy at work. I got the following email from someone who came across this blog. I asked her if I could post it so others could share her experiences. Here it is edited (minimally) and posted with her permission.
My reply:
Sorry about your awful experience, and sorry about the loss of your child. From what I know, the experience you had was one that is typical of people that suffer recall. Generally an emergency happens and anesthetic techniques need to be changed in a hurry, or things are so tenuous, that the risk of recall is weighed against keeping a patient alive. Trauma situations and obstetric situations are classic. I'm glad you had a positive conversation about this with your anesthesiologist. Still must have been a traumatic experience.
As for future surgeries, I think the mention that you had awareness during a D&C converted to a general anesthetic for a laparoscopy, (Just the description you gave me) should be sufficient to avoid any problems. They will probably have you go through your experience so that they can be a better picture of what happened. Some may request a copy of the previous anesthesia record to see exactly what medications you received, but I'm guessing most won't.
I cannot of course promise that this won't ever happen again(you may be resistant to some of our medications) but I'm guessing the urgency of the situation was the main cause of your period of awareness.
Hopefully your future experiences will be more pleasant.
I hate to ask this, but would you mind terribly if I posted an edited redition of your experience on my blog, so that I can post the advice.
Good luck with everything. I'm happy to answer any other questions, sorry for my delay in reply.
Her response:
This woman has had an awful experience, and has had the heart to share it with us. I think it illustrates that good communication between patients and physicians is of critical importance. It is especially important when "bad" things happen, though it should exist when things go well also.
Hi there,
I stumbled across your blog today and enjoyed reading your post about BIS monitors. I agree -- they DO NOT always work. I experienced awareness during anesthesia just last month, and my doctor was using the monitor.
I lost my baby during my pregnancy and needed a D&C. Unfortunately, my uterus was perforated during the D&C, and so the surgeon performed an emergency laparoscopy to repair the tear. I "woke up" feeling like I couldn't breathe, experiencing intense pain in my naval from the scope, and hearing parts of conversation in the OR around me. I was paralyzed, so I couldn't tell anyone what was happening. But I knew that if my belly was cut, something serious had gone wrong. I honestly thought that I was going to die. I eventually blacked out again for the remainder of the surgery, but have memories from pretty early after extubation (while still in the OR), and have much more recall of the recovery room than seems typical.
It had never occurred to me that something might go wrong with the anesthesia on top of everything else. (I figure that in the "Bizarro universe," my double has just won the lottery.) The only bright spot in this is that I ended up writing the anesthesiologist a letter describing what I experienced. He called me right away and said he was sorry, which was surprisingly helpful for me. He also said that when the perforation occurred, he'd had to quickly switch from using a mask to intubating me. From the details I described, he felt I woke up during that process. He said the BIS monitor lags real-time by at least a minute, and that while they are helpful, they obviously can't prevent all problems.
I do have a question for you: In future surgeries, how detailed does my description of what happend need to be to ensure I don't have awareness while under general anesthesia again? Any tips would be helpful.

My reply:
Sorry about your awful experience, and sorry about the loss of your child. From what I know, the experience you had was one that is typical of people that suffer recall. Generally an emergency happens and anesthetic techniques need to be changed in a hurry, or things are so tenuous, that the risk of recall is weighed against keeping a patient alive. Trauma situations and obstetric situations are classic. I'm glad you had a positive conversation about this with your anesthesiologist. Still must have been a traumatic experience.
As for future surgeries, I think the mention that you had awareness during a D&C converted to a general anesthetic for a laparoscopy, (Just the description you gave me) should be sufficient to avoid any problems. They will probably have you go through your experience so that they can be a better picture of what happened. Some may request a copy of the previous anesthesia record to see exactly what medications you received, but I'm guessing most won't.
I cannot of course promise that this won't ever happen again(you may be resistant to some of our medications) but I'm guessing the urgency of the situation was the main cause of your period of awareness.
Hopefully your future experiences will be more pleasant.
I hate to ask this, but would you mind terribly if I posted an edited redition of your experience on my blog, so that I can post the advice.
Good luck with everything. I'm happy to answer any other questions, sorry for my delay in reply.
Her response:
Hi again,
Thanks for the extra information. And yes, you can post my email(s) to your blog, in whatever edited version you want. I just request that you leave out my name.
The anesthesiologist for my surgery called me back again since I emailed you. He pulled my chart, and what he said matches up closely with what you surmised: Shortly after the lap began, my BP dropped. He administered ephedrine and lightened the anesthesia (propofol, I think he said?) to stabilize me. He believes this is when I initially became aware. He said that BIS readings remained in the 60s throughout the incident, which meant that I should have been out. I guess it just shows how hard it is to categorize levels of consciousness, even with a monitor. As a secondary
issue, he also wonders if I might metabolize Versed faster than normal, which would allow me to remember what happened.
It was a God-awful experience. I honestly thought I was dying, and you don't just immediately shrug off that sort of event afterwards. But, I don't really see how it could have been avoided. After doing some research and talking to both the surgeon and the anesthesiologist about what happened, I'm satisfied I got good care, despite my complications. So I am choosing to lump everything that happened to me -- the baby having trisomy 18 and dying, the uterine perf, and the anesthesia problems -- into the same category, which can be summed up as "sometimes you're lucky in life, and sometimes you are probability's bitch." I wish I'd been lucky.
Anyway, I'm hoping that this was a one-time bad event for me. For any planned surgeries, I'll follow your advice and explain my history as best I can.
Thanks again
This woman has had an awful experience, and has had the heart to share it with us. I think it illustrates that good communication between patients and physicians is of critical importance. It is especially important when "bad" things happen, though it should exist when things go well also.
Monday, February 20, 2006
sorry
Really i'm not ignoring you all. I've got some interesting stuff to post, but I just haven't had time to do it justice. It's coming!
Wednesday, February 01, 2006
On call
It's not quite 5 am, it's been quiet tonight. I'm on in-house call and the ORs finished really early. No pages since 9:30p or so. Thought it was turning into a great night. Of course I couldn't sleep. I usually can't sleep well at the hospital, but tonight's particularly bad, not even tired. Anyway started an exploratory laparotomy... we'll see what comes of it. I think the resident's happy to be doing the case since the resident that shares the call room snores.
Tuesday, January 31, 2006
Ludacris
I've blogged about medical lyrics in rap before... it's pretty interesting actually how medical words are thrown around.
Heard on the radio yesterday:
Jamie Foxx featuring Ludacris -- Unpredictable (luda's verse)
So Tylenol is acetaminophen whis is a mild analgesic(pain reliever) and an anti-pyretic (fever reducer). So while not actually a sedative... it can relieve your pain enough so you can sleep, or reduce your fever, so you're more comfortable and thus can sleep. I guess Luda's right still.
Heard on the radio yesterday:
Jamie Foxx featuring Ludacris -- Unpredictable (luda's verse)
I'll be your Tylenol just take me till you doze off
So Tylenol is acetaminophen whis is a mild analgesic(pain reliever) and an anti-pyretic (fever reducer). So while not actually a sedative... it can relieve your pain enough so you can sleep, or reduce your fever, so you're more comfortable and thus can sleep. I guess Luda's right still.
Monday, January 30, 2006
heart trouble follow up
negative heart cath.
This means the stents he got last year are still open. Doesn't really explain his minor chest pains. And we learned that I inherit my stubbornness from my dad
This means the stents he got last year are still open. Doesn't really explain his minor chest pains. And we learned that I inherit my stubbornness from my dad
Tuesday, January 24, 2006
Heart Trouble part Deux
So about a year ago when I started this blog, my father had just had a cath and seven stents... Tonight my mom called me and apparently a routine followup stress test was positive again. He's going in on Friday for another heart cath. Likely a restenosis of a stent from what my dad says. So I'm talking to him about he feels... and being the retired physician he is he notes that he only got a little chest pain when he exercised but was otherwise okay. I could have killed him. That's denial for you.
Anyway. Last year I was all about lifestyle change... exercise, diet modification, etc. Well i'm not exercising, though I do have an exercise machine, my diet is pretty much the same (off and on) we'll see what friday has to show.
Anyway. Last year I was all about lifestyle change... exercise, diet modification, etc. Well i'm not exercising, though I do have an exercise machine, my diet is pretty much the same (off and on) we'll see what friday has to show.
Sunday, January 22, 2006
Questions

Lately I've gotten some questions from readers and I thought I'd take the chance to answer some of them. I've been rather delinquent.
Some questions from some one beginning premed studies...
1)Any opinions regarding DO vs MD training particularly as it applies to anesthesiology?
Hmmm... interesting question. I think both avenues are good approaches to medicine, and they don't differ as much as you would thing, allopathic and osteopathic classes are almost the same with a few exceptions. I think in general MD programs give you more choices when you are choosing a what type speciality you want to practice in. I've trained with DOs and done a fellowship with a DO and find so generalities applicable. I will say in particular reference to anethesiology is that it seems to be becoming more competitive as a residency. Thus we are seeing less DO physicians meet the rigorous requirements for interview selection in my facility, but those we do see are amazing candidates. So I would have to say that doing well in school and getting high board scores are the most important requirements.
2) What is your experience with physicians who were non-traditional students (i.e. older -- I am already 30), again with particular reference to anesthesiology?
First of all, I do suggest to all my friends who are considering medicine as a career to reconsider it. It is a tough road with long hours of work and study. It is physically as well as mentally taxing. There are better ways to earn money, influence, and/or respect. Saying all that, if you are one that really wants to be a medical professional, who am I to stop you? I do love my job, but the road to where I am now has been a rough one. I would however do it again.
Next, I don't think being a non-traditional/older student necessarily puts you ate any sort of disadvantage in being selected for a residency program. I think it provides an interesting perspective in the field of medicine. Being older, I think the physical demands of medical training may be more difficult. Also there is more likely to be a family involved. And that has needs of its own. All that is fine though, many people train in the medical field with large families. It just requires more juggling.
Just think though if you're considering anesthesiology at age 30 and start medical school in the next few years you may be 40 or older before even starting to have the opportunity to practice on your own. That time is valuable and it is quite a commitment. In reference to anesthesiology, there are plenty of older residents, some have completed all or a significant portion of another medical residency (anesthesia is a field that is highly switched into), some have just gotten a late start as you have. Also anesthesia is demanding, but may require less time commitment in residency some places, then say other residencies such as surgery (although there are wide spread work hour limitations)
Another question from an electrical engineer.
3) How accurate are the new monitors that are supposed to indicate depth of anesthesia in a patient?
That also is an interesting question. The device you're most likely referring to is the Bis monitor. It's gotten quite a lot of press lately. It's basically a transcutaneous monitor that picks up electric activity from the brain (EEG), performs a complicated "black box" calculation and spits out a number ranging from 100 (awake) to 0(No electrical activity). We do not use this device at our institution. There are several problems that I see. First of all there are plenty of other ways to measure consciousness clinically. The device and disposables are not inexpensive. Also what bothers me the most is that the calculations that are performed by the devices are a proprietary formula, and we are not privy to those aspects. I'm not sure how accurate thes e devices are, but regardless I'm not sure they're necessary. (just one man's opinion) | 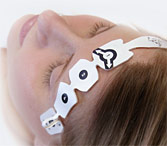 Picture taken without permission from Aspect Medical Systems, Inc. website |
If I missed your question, let me know I'm trying to keep up.
Monday, January 16, 2006
IV starts
Bit of a strange couple of days for IV starts for me.
Two nights ago one of my roomies went on a bit of bender and thus couldn't keep any food or water down yesterday. I started an IV on her at home, instead of her going to the ER and waiting for hours and having the same thing done, except with a large bill.
Today near the end of the day one of my residents requested I put an IV in her because she wasn't feeling well and had some sort of flu bug... I was going to put in for her to go home early, but she was relieved by a late resident anyway. What a trooper.
Anyway, wonders that a couple liters of fluid will do to help with how you're feeling.
Tuesday, January 10, 2006
More anniversary stats from the last year
Shortest time between posts: 3 minutes
Longest time between posts: 17 days
Longest time between posts: 17 days
Sunday, January 08, 2006
Anniversary
Three days ago this blog turned one year old... It's been a slow year and a fast year at the same time.
I've finished a cardiothoracic anesthesiology fellowship. Started a full time job as a cardiothoracic anesthesiologist. Bought a house.
On the other hand... I am working today on a sunday, doing a semi-emergent (as in booked two days ago) coronary bypass. (well supervising a resident anyway). This after doing a Heartmate II and a heart transplant on Friday, two chest closures yesterday (see friday's cases). At least I have tomorrow off.
Some stats:
365 days.
72 posts.
Avg. 1 post every 5.07 days.
5006 vistors by counter since March 7, 2005 (when I started counting) some of those are me however.
I hope for many more years.
Wednesday, January 04, 2006
Tuesday, January 03, 2006
Readily available
I'm trying to be a good anesthesia attending today... but failing. I flew back late last night from being out of town for the New Year. The anticipated late arrival after the weather delay and the walk through baggage and the shuttle bus to the parking lot and the drive home became the ridiculously late arrival. Got settled at home and slept for only an hour before coming in to work. Good thing I slept on the plane. I am working with 2 senior residents today. Both very good. Both rooms I'm supervising have long cases, so not much to do after getting started. Instead of teaching I've been hanging out in my office. Being "readily available" for crises from my chair.
Wednesday, December 21, 2005
Almost one year.
I just noticed that this blog is almost one year old... I think i've changed a lot since this whole thing started. We'll have to have some sort of party.
Monday, December 19, 2005
Hmm...
Found out today that there's a Center for Vulvar Diseases here at my institution. Forgive me if you suffer from a vulvar disorder, but I didn't realize there was such a prevalence of disorders that there needed to be specific center for it. If you don't know what a vulva is... you shouldn't be reading this (or look it up)
Sunday, December 18, 2005
Christmas Party
Work Christmas party last night. Funny no one is even remotely recognizable in party clothes. You have to visualize them in scrubs before you can associate a name with a face. Weird. I didn't drink too much which is good.
Where does one conscience go under anesthesia?
I was recently asked by a reader (weird to say that... thanks for reading)"Where does one's conscience go when you put someone under?" It's not a question easily answered. One that scholars and theologians probably as well have tried to answer for millenia.
First of all not to nitpick but you probably mean consciousness, meaning sense of one's personal or collective identity, rather than conscience, meaning source of moral or ethical judgement. I only clarify this not to be a jerk, but to make sure we are on the same page.
I don't know if there's really a right answer to this question... First. Is this is the same quesion as "Where does one's consciousness go when I sleep?" Probably in my opinion. Anesthesia is induced sleep (more or less... i can give you a more techically specific definition but that will just be cumbersome in this metaphysical question)
Most would say one's consciousness is just supressed while you sleep or are under anesthesia... it's there but it's unable to express itself or take in new information.
More religious people would say it's there watching over you. A "soul" if you will.
Which is right? I don't know. Is there another alternative? I think the best thing would be to leave it comments and see what people have to say.
Monday, December 05, 2005
Level 1Trauma
This weekend I was on cardiac call... I had to be available for any cardiac cases going on over the weekend. This can be a hit or miss call, sometimes you're in the hospital all weekend, sometimes you're at home all weekend. It had been pretty quiet til then... early out(ish) on Friday, nothing on Saturday. Then my pager went off Sunday morning at 4am. nothing good about that. Apparently some sort of penetrating trauma case that required my attention. Well usually level 1 traumas refer to emergent cases, often going straight up the OR once they arrive at the hospital. I was confused. You don't want to wait for me to drive in (newly and still falling snow) to take care of an emergency, the in-house people will take care of it.... No no... they were stable enough to be transferred from another hospital, then stable enough to go to the CT scanner, now stable enough to wait for the cardiac team to come it. Still it's an emergency. "Ok i'm on the way in"
Now I'm always kinda pissed off when I get called in... half the time I get called in for cardiac it's nothing critical (i know that sounds weird) Someone freaking out for no reason. I know it's my job to be available when they call me in, so I don't think i should be angry.... I still am. I figured if that bullet were anywhere important they'd be dead by now. I'm also mad for other people too. I think "Heaven forbid if anyone gets hurt driving in the snow coming into the hospital for this non-emergent 'emergency' "
I slip and slide my way in. I see the cardiac surgeon in the pump room. I say "hi, what's going on?" He says "I don't know... they told me she was dying and to come in, now we're waiting... i don't know what doing..." Great now the cardiac surgeon and I both don't know what's happening. Oh well easy enough to blame the Trauma service.
The patient finally shows up. Very stable. We put some invasive monitors and access into the patient. I don't see much blood in the pericardium (sac around the heart) on echo. There is some though... not much. Surgeon says it probably looked like pericardial fat because it was well-organzied clot. They take a closer look at the heart... this lady's lucky. The bullet went through the pericardium nicked the right side of the heart and kept going. A half-centimeter another direction and that nick would have gone through one of the coronary arteries and the patient would have bled to death or part of the heart would have completely stopped working. Lucky.
I feel bad now that I was angry driving in.
Wednesday, November 30, 2005
PACU
(Trying to catch up on old ideas... this actually happened last week... pretend it's today.)
Not a typical day for me. I was the faculty covering the post-operative recovery unit. It's actually not a particularly tough job most of the time since there is a resident assigned to field most questions and problems. There's the occasional problem... nothing big today. Staffing ECTs. (electroconvusive therapy) Done three times a week in the PACU. Signing patients out (i.e. administrative whatever-you-want-to-call-it)
One thing that was unusual was that we had two physicians come through as patients. I guess doctors need surgery too. Didn't want to give special treatment, but did stop by and say hi to both the pediatric anesthesiologist and the cardiac surgeon (who spent the previous saturday on a stretcher in the pump room while his partner finished a surgery they had started together).
Tuesday, November 29, 2005
Bladder cancer
Had patient here this AM for a cystectomy (bladder removal) for bladder cancer. A tough man... clearly trying to hide the fact that he is terrified (rightfully so.. a big operation) Among the last things he said before going to sleep (taken anonymously without permission.)
I'll be badder without a bladder!
Saturday, November 19, 2005
Tough Day
Thursday was a tough day. I was the cardiac faculty on call, so I knew from the start it was going to be a long day. I came in early because there was a conference on echocardiograms that I wanted to go to. Anyway I was wandering in, and my pager went off... never good in the morning. "Case going on in room 7" I change quickly and get in there. A heart transplant. Just starting really... It's patient with bad heart failure that has a Heartmate (a type of left ventricular assist device). Of course he's had about three previous heart operations so there's lots of scar tissue in the chest makin the operation much more dangerous and complicated.
Anyway... the new heart is in the patient about 3 pm or so. It's not going well as we come off bypass, but we're doing reasonably. All of a sudden, the blood pressure drops and I see a bunch of air on the echocardiogram. Part of the hears stops functioning well... So I assume some air has gone down one of the coronary arteries. We crash back on bypass... Left heart starts functioning a bit better but now the right side doesn't look so well. We end up after struggling a bit assisting the right side of the heart with Abiomed right ventricular assist device. This are settling out, the all of a sudden the left side of the heart is starting to look bad.... Now a discussion ensues on if they need to put the patient on ECMO (extacorporeal membrane oxygenation). Ends up they endup supporting the left side of heart with a left sided Abiomed.
Now we are supporting both sides of the heart, and the patient is relatively stable We're pouring clotting factors and blood so the patient will stop bleeding. They'll try to wean the patient off assistance early next week. So this patient came into the hospital with a bad heart and a Left ventricular assist device... now has a different heart and assistance for both sides of the heart. Only time will tell. By the way it's 9pm we're finally done. a quick 16 hour case. I'm so exhausted.
Sunday, November 13, 2005
Interviews
As a new attending... I got to participate in resident interviews for the first time. As a resident, I did attend a lot of interviews, and I gave a lot of tours. On the other side it's a little weird. I don't know if I like having any influence at all on people's futures. I can say that the applicants as a whole were insane... everyone had great (not just good) board scores, publications, etc. I can't say that I would have gotten into this residency program now if my life depended on it. Seems though overall that people were pretty nitpicky. Which is okay I guess. We're trying to stratify a couple hundred really top-notch applicants. Don't know if I was too harsh or not. I guess my rankings were close to everyone elses.
Friday, November 11, 2005
Make a wish
Okay... I NEVER watch the news. nothing ever interesting is going on. especially when I can read things on the internet. Especially never local news. Unless I want to see a skateboarding bulldog or a waterskiing squirrel. Anyway, my roomate was watching something and the news was on after it. And they started talking about the make-a-wish foundation and so on. So I was about to turn the channel... then they mentioned an 9 year old and a name I recognized. It was a generic name and could have been anybody, but there he was, a child I took care of as a cardiac anesthesia fellow.
The reason I remember this kid is that he was truely one in a million. The surgery he was having as an eight year old was a coronary artery bypass. He had a disease called hereditary familial hypercholesterolemia. The problem for this kid was that he had the worst kind. He had cholesterol levels 8 to 10 times what a normal person would have, thus he had premature disease of the arteries feeding his heart. Most patients who have this type of surgery are in their fifties and above.
What killed me was that on the news report they did say he had coronary artery disease, but they said that "Sometimes he doesn't feel well" and left it at that. I guess you can't say "Sometimes his heart doesn't get enough blood" on TV. Well at least he got a new puppy.
Tuesday, November 08, 2005
More Prisoners
So I was on call again last night, and we had a trauma flown in. Now this is not completely unusual, since we are a major referral center, but since the town in relatively suburban, not a lot of violence. Anyway a prisoner apparently had barricaded himself in his room and cut his neck from the middle of the neck to the ear with a razor blade or something. This seems weird to me for several reasons. One, seems like prison is all about being barricaded into places whether you like it or not, so the part where he barricades himself somewhere is weird. Second, I thought you weren't allowed to have razors in prison. Next... you'd have to be pretty determined to slice yourself that wide open. ouch.
Now I understand this guy is a violent criminal, but they bring this guy up to the OR... he's intubated and paralyzed... big wad of bloody bandages on his neck... but despite this fact he still has his arms shackled to his waist. Like he's getting anywhere while he's paralyzed. Then again with the sitting outside the OR while he's under general anesthesia. Oh well. I'm sure the guards are just doing what they're told.
Good news for us, he didn't hit anything too big that we couldn't control the bleeding. (plus they had time to fly him in from up north in the helicopter). Bad news for him... seems like he didn't feel like living anymore.
P.S. I was ending another case with a CRNA and she had only heard part of the story so she only knew we were operating on a self inflicted neck wound. So she said "Life can't be that bad can it?" I then mentioned that he was a prisoner apparently in prison for violent crimes. She then seemed embarrassed "I guess it can be that bad." I chuckled. (proves again -- I'm a bad man)
Tuesday, November 01, 2005
prisoners in the OR
Had a prisoner as a patient the other day. It was very surreal as always. having two armed guards sitting next to the patient instead of family members. Also the leg chains have some sort of surreal quality to them also. A fellow faculty has the habit of looking up these patients on the Department of Justice homepage. Apparently you can just look up anyone with a criminal record or is currently in prison. I prefer not to know. I think I would be a better person than to let the knowledge of his crimes affect his care, but I prefer not to leave that to chance. The man seemed very nice. Also weird is the insistence that they sit outside the OR for the entire surgical procedure. Like they're going to get off the table and run out while they're under general anesthesia.
A couple of years ago I had a patient undergoing cardiac surgery he was in his mid-seventies. Apparently he had been in prison for twenty or more years. He was a pretty feeble man... still those guards were there sitting outside the OR for the entire case. I really don't know what he did if he had been in prison for that long. He also seemed very nice.
A couple of years ago I had a patient undergoing cardiac surgery he was in his mid-seventies. Apparently he had been in prison for twenty or more years. He was a pretty feeble man... still those guards were there sitting outside the OR for the entire case. I really don't know what he did if he had been in prison for that long. He also seemed very nice.
Monday, October 17, 2005
Awful
I'm an awful person. I was bringing a patient the the intensive care unit and I was looking for the nurse practitioner or resident to take report so I could get out of there. anyway, popped my head into one of the beds and it was an ECMO patient (extra-corporeal membrane oxygenation). Basically ECMO is complete support for the heart and lungs when they are not working well (it can also be used for just lung support). It consists of a pump and an oxygenator to take over both functions. Anyway... the patient was going down later today for a procedure and the nurses were wondering if anesthesia presence was going to be required or not. Sometimes procedures are done without anesthesia personnel if the patient is doing well, so I said "I hope not, they're Stable on ECMO aren't they?" I then shook my head wondering what I had said. The phrase "Stable on ECMO" is almost an oxymoron given that they patient is NOT stable thus needs the almost complete support of ECMO. I've spent too much time in the hospital.
On another note, the cardiac case I'm supervising finished early today. Which is good, but it's bad because that means our room is open for add-on cases which are always always always a mess. But our OR bed is broken so I'm hoping nothing comes. I'm a bad man.
On another note, the cardiac case I'm supervising finished early today. Which is good, but it's bad because that means our room is open for add-on cases which are always always always a mess. But our OR bed is broken so I'm hoping nothing comes. I'm a bad man.
Sunday, October 16, 2005
Music in the OR part deux
So I don't know if many people at work actually know about this blog. Just a few I hope. anyway not minutes after I post the last post about music in the OR... I get an email from someone in the department. It's one of those with a million headers in the email so it's been forwarded a billion times.
Anyway... it linked to a version of the article and asked why would anesthesiologists cooperate with publicity that that makes it look like they have nothing better to do in the OR other than play music. I never really thought about it that way. We usually are busy doing other stuff. still having a choice would be nice.
On a completely random note, had a pretty decent day on Friday. Working with two very good, very pleasant residents. One paged me because our "healthy" patient had just had a run of V-Tach... for those of you who are non-medical. It's heart rhythm that's potentially fatal if it persists and is untreated. Luckily in this instance it was short and self limiting, but we were sending off some lab tests to make sure it wasn't a fairly simple electrolyte problem. Anyway I threatened the resident with a bad eval if it happened again. I told her I would note on her eval that, "Resident was good to work with, very knowledgeable, but unfortunately arrythmogenic" (irregular heartbeat-causing) She laughed.... I think she was humoring me... then again she laughs at everything.
Tuesday, October 11, 2005
Music in the OR

Image provided by Freefoto.com
A friend of mine sent me this link...
Are anesthesiologists the DJs of the operating room?
At my hospital the surgeons have control over the music. No choosing by me. I don't think they'd like my music anyway. Hip hop and pop is probably to contemporary for the ORs.
There is a lot of music in the ORs... You can tell what kind of day you're going to be having depending on the music. Country in the Vascular rooms, a little bit of everything in the Neuro rooms... quiet only in Cardiac... music maybe when they're closing.
Sunday, September 25, 2005
House
I'm not one usually to watch House M.D. on TV, but i was over a bud's and was forced to. It was the most unrealistic episode ever. Many strange procedures in the name of making a strange diagnosis. I'd review it but I'd be reworking something already done...
Check out the House review at Polite Dissent
Check out the House review at Polite Dissent
Tuesday, September 20, 2005
Enthusiasm
Worked yesterday with one of the most enthusiastic residents in the program. He's a good guy, but sometimes needs to be taken in small doses. I can't say anything bad about him really, he's a genuinely nice guy.
We were in the cardiac room... staffing is one on one in cardiac in our institution meaning we supervise only one cardiac case at a time. The second cardiac case of the day was supposed to be there already so they could get some invasive lines placed preoperatively. Usually the timing in such so that the most critical portion of the cardiac case is happening while I need to be surpervising those lines elsewhere. Anyway, came off of bypass in the OR, then finally then next patient was ready to get lined. After the lines were placed, I got back to the OR and they were about to transport the cardiac case to the ICU.
I told the resident to go to lunch (we give the breaks when we staff one on one) because I figured that i would get a chance for a couple more hours if he didn't go right away. He came back about 10 minutes early and met me in the ICU. Apparently he had bought me lunch and left it for me down in the anesthesia offices. Way beyond the call of duty... I suppose it's good for brownie points, but I don't believe he did it for that reason. I believe he did it just because he's a nice guy.
Glad there are still people out there like that.
Friday, September 09, 2005
Tuesday, September 06, 2005
Whoa
On call for the 1st 72 hours of labor day weekend. (Friday through Sunday) Had to work about 14 hours on Friday, otherwise dodged a bullet. No calls to come in for cardiac cases.... I imagined it would have been pretty busy. Not that I'm complaining
Wednesday, August 31, 2005
Bier Block
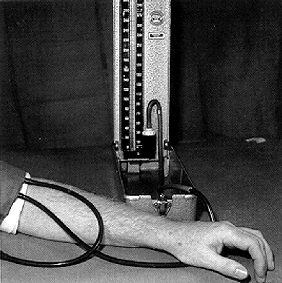
Image used without permission, property of original owner
We did a Bier Block yesterday. My new resident was very excited about it... I don't know if he's just an enthusiastic person or if the procedure was all that interesting. I guess we don't do that many of them, plus he's kind of new. Actually it's probably him... he IS very enthusiastic.
For those of you not familiar with the Bier Block it's named after Karl August Bier... some German guy who invented the technique in 1908. It's also called an intravenous regional anesthetic. It's useful only for surgeries on the extremities. Basically you put a pressure cuff on the arm, use a rubber bandage to squeeze out all the blood out of the arm. Then you inflate the cuff and inject local anesthetic into the arm (through an IV you've placed earlier in the hand) The arm stays numb as long as the cuff is holding the local in the arm. This works because in general nerves travel along with blood vessels in most of the body. So if you fill the vessels with local anesthetic, you also anesthetize the nerves.
Anyway now if I can just get that resident to stop calling me "Sir" we'll be in good shape.
Tuesday, August 30, 2005
Hurricane Katrina

Images from AFP/NOAA-HO used without permission
I'm watching the coverage of the damage caused by Hurricane Katrina. Makes me glad I live in the north... Makes a lot of my problems seem insignificant.
Interesting to hear that many more will die in the aftermath from lack of power and water and food etc.
Tragic. Mother Nature is a vengeful woman.
Friday, August 19, 2005
Avoiding the pain of death
Got a call this morning from a friend. One of her patients had died. She was distraught to say the least. She is a resident in an obstrectrics/gynecology program. Her patient was having a baby by caesarean section. Apparently she went into some sort of respiratory distress, and did progressively worse. It was my friend's second death as a physician. She specifically told me that she went into OB/Gyn just so she wouldn't have to deal with death. I honestly had nothing to say to her. First of all I don't know how to talk to crying women. Second of all, She really had a right to be upset, there's really nothing to say. She really does put herself into her job.
This has been much different from my experience. I of course am in a different field. There is much more "volatility" in anesthesia. We deal with critical patients all the time. I, myself, have had particularly bad luck in this respect. I watched one of my patients bleed to death on my first day of anesthesia residency. It was very traumatic. I considered not coming back for a second day. Then I realized that was part of the job that I come there to do. I still remember that day vividly. I don't think i've had a case that bad since. I also had a patient die my first call as a attending staff. We did everything we could to keep that patient alive for three hours, but nothing helped. That was also very "character-building".
So how do we avoid death as physicians? The only way I can think is to avoid taking care of patients. I could quit tomorrow to drive a cab or work at Blockbuster. At what cost? I could throw away years of schooling and hard work, I could throw out the desire to practice good medicine. Unacceptable. I enjoy my work, but as a result I need to be able to deal with death. Hopefully not very often though.
My friend needs to learn this too... I think she'll come around. She's worked hard to get where she is... unfortunately she's pretty miserable these days. Hopefully as she gets further into her residency she will enjoy her work as much as I enjoy mine.
Sunday, August 14, 2005
Monster Garage
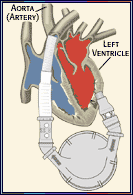
Image taken from Thoratec Corporation website without permission. Image property of Thoratec Corporation
I've been a full time cardiac anesthesia staff now for about a month. I thought I would be spending more time in the heart room, but it only ends up being about one day a week. Oh well. i don't mind the general ORs.
Wednesday was an interesting day in the OR. Two big cases by the newest cardiac surgical staff -- he just started in July, the same time as I did. They're giving him pretty big cases even though he's the most junior. Maybe it's a way of breaking him in or something. I don't know.
Our first case was an exchange of an abiomed LVAD for a heartmate LVAD. LVAD stands for left ventricular assist device. It's type of support to help the heart when it can't function well enough on its own. The difference between the two devices is that the first is a mini-fridge size device that sits next to the bed and has tubes connecting it to the heart... the second is an implantable device (think softball sized tuna can) connected to the heart to help pump. Patients with this devices can even go home. Mostly it's used as a bridge to transplantation. It wasn't a terribly long case, but it can be complicated. There's multiple vasoactive medications, nitric oxide, and a transesophageal echocardiogram to deal with. Also a tangle of IVs and lines. Went very well though.
The second patient had an even sicker heart. He had a Heartmate LVAD(see above) supporting his left heart and a abiomed RVAD (right ventricular assist device) supporting his right heart. He had recovered enough function in his right heart to have the RVAD removed. There's no cardiopulmonary bypass, but you have to deal with the possibility of a lot of bleeding. ALso the possibility exists that the right heart isn't ready to come off support yet and will fail after you cut off support. Again it went pretty well so I can't complain. But there's a lot to think about and take care of. I guess that's why I like being in the cardiac ORs
Monday, August 01, 2005
Dinner with my mentees
Had dinner tonight with my mentees. They seem like a couple of good guys. I wanted to say all things considered, if I'm a horrible mentor, that at least I took them to dinner. Apparently some if the other CA-1's are jealous, because they don't even know who their mentors are or they haven't had any contact yet. I hope i'm not making anyone look bad. It's just something I wanted to do.
Thursday, July 28, 2005
horrible
had a horrible day today. couldn't start an iv, an aline or an epidural to save my life. worse yet, wet tapped that same patient (a complication from placing an epidural for those non medical types). argh. luckily i killed no one. ended up with a femoral aline and several neck lines (several patients)
(apologies for the extremely lingo filled post. had to vent.)
on the plus side went to have arab food with my buddy who finished his cardiac anesthesia fellowship. it was a good time, tasty food, good conversation, damn road construction detours though.
(apologies for the extremely lingo filled post. had to vent.)
on the plus side went to have arab food with my buddy who finished his cardiac anesthesia fellowship. it was a good time, tasty food, good conversation, damn road construction detours though.
Thursday, July 21, 2005
new residents
I showed my new residents how to put together an IV tubing setup today... they seemed extremely excited. i guess i take the easy things for granted.
Heard from a resident in the ICU
(ECMO = Extracorporeal Membrane Oxygenation... more on ECMO another day... so complicated)
Heard from a resident in the ICU
ECMO is easy, you just got to keep them from bleeding to death, and keep them from clotting to death.
(ECMO = Extracorporeal Membrane Oxygenation... more on ECMO another day... so complicated)
Thursday, July 14, 2005
Insanity
I sat for my boards (for the second time) last Saturday. I can't say i feel any better about compared to the first time. We'll see i guess. In my post boards insantity I invited the whole anesthesia department to my house for a BBQ. We'll see how many show up... I hope people show up, I can show off my messy new house, but I hope there's not too too many people.
Thursday, July 07, 2005
Mentees
I just got assigned two new anesthesia residents as mentees... I guess that makes me a mentor. Scary huh?
I am wondering why if there are dozens of faculty members why I got assigned two residents out of twenty-four to be mentees. Whatever... I don't really mind.
I am wondering why if there are dozens of faculty members why I got assigned two residents out of twenty-four to be mentees. Whatever... I don't really mind.
Saturday, July 02, 2005
First Day?
Technically, i believe that friday was my first day as an attending. I've had very bad luck on other first days of sorts. I had a patient die on my first day of residenc. And there have been many almosts on other various first days. No one one died. Yay. One guy did "accidentally" blow off part of his face with a shotgun. very unusual for this town. very lucky for him if it was truely an accident despite the fact he lost an eye. Hope people have a safe holiday.
Sunday, June 19, 2005
Graduation
Yesterday I attended my last graduation. Probably not the last one i'll be at, but the last one for me.
At the end of the month, I am no longer a cardiac anesthesiology fellow... I am a cardiac anesthesiology faculty.
A little bit of a strange feeling. Last year's graduation from residency was more significant. A bigger milestone, and I won an award I wasn't expecting. But it wasn't the end. I knew there was more.
Now there's no more. Just the "real world"
Scary.
happy dad's day

Thanks for all you've done.
What do you get the man that's made it possible for you to have all that you need?
My dad got DVDs. A small token. Thanks
Monday, June 13, 2005
Tamponade
(preamble: I've been told by a good friend that sometimes my stories feel like they are over her head. I'm sorry. Most of these anectdotes are written for medical professionals rather than the lay person. But I don't want to exclude the lay person so I'll try to explain more as i go along. Sometimes though the stories need to be written in a technical way. i'll try to do better... today's story will be technical.... i'll call you later and I can clarify things)
I've been on cardiac call this weekend (as faculty). This means I sit at home waiting for my pager to go off, dreading any possible emergency cardiac cases that come in. I'm usually a wreck all weekend for two reasons. One, i know as soon as I plan to do something like meet friends for lunch or go to a movie, Murphy's law will kick in and I will get called in. Two, as a relatively new cardiac faculty, I'm probably not as confident in my skills as I should be and I have doubts about whether I can handle what comes it.
At 2:45 this morning. I get a page... "emergency bring-back bleed.... phone number blah blah blah" I call in and someone's coming straight down from the ICU. Now this isn't all that unusual. People have heart surgeries all week long, and sometimes they bleed more than they should afterwards. They ooze for a few hours, they are indecisive about coming to the OR... finally in the middle of the night they decide they've had enough and need to operate. They come down to the OR, the surgeons poke around a little and they use their electrocautery to buzz a few little blood vessels, say they can't find much, and then you go back upstairs. No big deal. The reason this is considered an emergency is that there is a possibility that there is a major bleed somewhere and it can compromise the way the heart functions. The heart can stop working because there can be blood clot all around it (rather than blood pumping through it)
So I assume it's one of those slow oozing bleeders, but you need to come in anyway and take care of the problem. I roll out of bed, do my best to fix my bed head and hop in the car. I'm at the hospital within 15 minutes, and changed in the locker room less than 10 minutes later. I walk into the OR expecting the nurses to be setting up and waiting for me to bring the patient down. Instead I see the general call residents and staff hovering around the patient. She's pale looking and her eyes look like they're half rolled back in her head. Now I'm thinking "aw, crap... this is for real" The cardiac surgery resident is throwing a few lines and we're scrambling to get this patient ready for surgery.
Now this is one of the special circumstances in anesthesia. You need to have the patient ready for surgery BEFORE they go to sleep. These compromised patients are using all their reserve to keep up their blood pressure, catecholamines rushing though their systems, peripheral vessels clamped down, all trying to compensate for this unstable state. When you put them asleep this relaxes their compensation and they can "crash" as soon as they're asleep. Also our medications to put you asleep tend to lower your blood pressure too. So to combat this, you have them prepped and drapped for surgery with the surgeon standing there ready to operate as soon as they are unconscious.
The cardiac surgeon pops his head it to see what's going on. His resident lets him know that this is the heart transplant patient from earlier in the week and that they need to get started NOW. They wash hand quickly while the nurses rush to prep the field. The drapes go up. And they let me know they're ready. I put the patient asleep and they get started immediately. My anesthesia resident puts in the breathing tube under the drapes and the surgeons open up the chest. Immediately you can see blood welling up out of the chest and a squirting bleeder. Immediately the blood pressure drops. We've lost about 2 liters of blood in about 10 seconds. We get the rapid infuser going and pump in some blood quickly and I give the patient some epinephrine(one of our stronger drugs) to get the blood pressure back up. Luckily they get the bleeder under control and about 2 hours later we get back up to the ICU.
We were pretty lucky today. I can help but think that if it had taken me 10 more minutes to drive in, or that if the team in the hospital hadn't been so proactive in getting the patient to the operating room that this lady might be dead. I'm relieved.
It's 530 am. I'm tired, i'm thinking of going home. I over hear the cardiac surgery resident, "blah blah blah accepted a lung transplant blah blah blah..." I know I'll be back later today.
Monday, June 06, 2005
Running
Tomorrow i'm staffing a thoracic room and an ENT room.
The thoracic room has two moderately sized cases... requiring epidurals and alines.
The ENT room has 6 short cases, at least 2 requiring awake fiberoptic intubation.
The kicker? The two rooms are about as far apart as you can get in the ORs. My room assignments got switched today because they opened up a 3rd cardiac room. I'll be running my ass off tomorrow. If i'm smart i'll pack a lunch. I probably won't though.
Sunday, May 22, 2005
Happy Birthday Morphine!
Apparently Morphine turned 200 yesterday. I forgot and didn't buy a present.
Kelly did not forget and collected some anecdotes in honor of morphine's birthday.
I'll send a card later.
Kelly did not forget and collected some anecdotes in honor of morphine's birthday.
I'll send a card later.
Wednesday, May 18, 2005
Tangled Bank
Tangled Bank for the week is up at the Chronicles of a Medical Mad House. The Tangled Bank has evolved over the year to include medicine and topics closely related to science. If you read my blog you've read my entry already, but check out the others!
Wednesday, May 11, 2005
Blogging when people you know read your blog
Just read a post from an article about tips for bloggers (from the Right Wing News) Last on his list...
I know at least 2 people at work know of my blog... should it affect how I blog... probably not. Does it... probably. I not only have to worry about getting fired. I have to worry about being sued and patient confidentiality. I don't blog at work.
Coincidentally... a friend of mine who has an incredibly insightful blog (and she didn't want to tell me about it -- I haven't linked to her at her request) said yesterday.
I think it affects what I write as well. One of the comments from the first article said it best.
Blog on.
25) Given that there are plenty of people who've been fired or disciplined at work either for blogging on the job or for something they said on their blog, the fewer people at your job who know about your blog, the better.
I know at least 2 people at work know of my blog... should it affect how I blog... probably not. Does it... probably. I not only have to worry about getting fired. I have to worry about being sued and patient confidentiality. I don't blog at work.
Coincidentally... a friend of mine who has an incredibly insightful blog (and she didn't want to tell me about it -- I haven't linked to her at her request) said yesterday.
Even now, I am concious of what I write because of those who know about it or have ever visited it that may know me.
I think it affects what I write as well. One of the comments from the first article said it best.
Blog because you want to, ...It's the passion that readers will respond to.
Blog on.
Sunday, May 08, 2005
Thursday, May 05, 2005
Vomiting Ferrets?

Fidgett the ferret (maybe it's Waffles the ferret... i don't know them so I can't tell) from ToyKeeper.net. Images used without permision
Today while hanging out with some of my smart friends, I learned randomly that ferrets apparently are used in lot of research for nausea and vomitting. I thought this to be rather strange. I also began to have images of a cage some where with liitle piles of ferret vomit in the corners.
I began also to wonder why this is. So I went to our friend the internet...
Most animal research on nausea is performed on ferrets, apparently one step up the evolutionary tree from rodents, which do not vomit.
-- From Palliative Care Perspectives, James L. Hallenbeck, M.D.
Saturday, April 30, 2005
Juggling

Logo of the 6th Swiss Juggling Convention, in Zürich 1992, used without permission
So I feel like I'm not getting enough done.
I'm trying to buy a house, do a good job at work, study for boards, read to prepare for talks, plan a vacation with some college friends... all while trying to get enough sleep and also not go insane, which means decompression time.
Mortgage insurance, home inspection, radon, homeowners insurance, down payment, closing costs, argh!
They say life events are very stressful. Several are going on now. I don't even have kids or a wife or girlfriend to distract me. I've been neglect the cat. I don't know how some people do it. They are amazing.
Damn, I need a haircut too.
Sunday, April 24, 2005
Board Review

Image used without permission from USGS via Wikipedia.org
Just got back from an intensive 3 1/2 day Board Review Course in Chicago. It kicked my butt. I hope I'm ready in 10 weeks. I've gotten great traning in anesthesia, but I still don't feel ready to take the boards (again). The course was worth the extensive fee though. We'll see if it was really worth it when I get my scores.
Sunday, April 17, 2005
Trick Daddy
I may be the only anesthesiologist that listens to rap. It's good stuff. It's amusing though... occasionally they throw in that random medical term in.
Lately on the radio they've been playing (Gimme Some) Sugar(remix) by Trick Daddy, featuring Ludacris, Lil' Kim, and Cee-Lo. It's a great song. They have some amazing rhymes.
One verse by Lil' Kim goes "I give ya high blood pressure like a diabetic". I know they're trying to relate the diabetes theme in as the title is Gimme Some Sugar, but I don't know that diabetes cause hypertension. They are associated however it seems. I guess she's saying she's so hot she raises your blood pressure.
Oh well, I can't hold it against them. I still like the genre. I still like the song.
Thursday, April 14, 2005
Litigation
Today we heard about a case where something had been done that had litigation potential.
There are several things that would have to occur to make this a successful suit.
First of all, it requires a bad relationship with the patient. In this case, it was fully explained to the patient, and the procedure to correct the problem was immediately arranged. The patient seemed very understanding. For the second reason we need to go to my lawyer buddies.
A tort is a wrongful act other than a breach of contract that injures another and for which the law imposes civil liability. There are four elements of a tort as I understand it
If all four are not present a tort should not be successful. In this case, there was a duty, and that duty was definitely breached. Most of the time, the act in question does not involve arguing breach of duty, it is assumed to have happened. There also needs to be damages or harm associated with the breach of duty, and the damages must be caused by the breach of duty. If there is no damages, there is no tort. If there are damages, but no causation, there is no tort. In this case, there were no damages to the patient other than having to go through the corrective procedure. So there should no sucesful tort possible.
looking through my visitor statistics, apparently I'm the 27th choice for a google search of the movie SuperSize Me. Interesting.
There are several things that would have to occur to make this a successful suit.
First of all, it requires a bad relationship with the patient. In this case, it was fully explained to the patient, and the procedure to correct the problem was immediately arranged. The patient seemed very understanding. For the second reason we need to go to my lawyer buddies.
A tort is a wrongful act other than a breach of contract that injures another and for which the law imposes civil liability. There are four elements of a tort as I understand it
- Duty
- Breach of Duty
- Damages/Harm
- Causation
If all four are not present a tort should not be successful. In this case, there was a duty, and that duty was definitely breached. Most of the time, the act in question does not involve arguing breach of duty, it is assumed to have happened. There also needs to be damages or harm associated with the breach of duty, and the damages must be caused by the breach of duty. If there is no damages, there is no tort. If there are damages, but no causation, there is no tort. In this case, there were no damages to the patient other than having to go through the corrective procedure. So there should no sucesful tort possible.
PS. Hmmm...
looking through my visitor statistics, apparently I'm the 27th choice for a google search of the movie SuperSize Me. Interesting.
Tuesday, April 12, 2005
Monday, April 11, 2005
Difficult Airway
So as a fellow I usually just help out where I can. I'm at the point in the fellowship where I staff rooms as the attending about twice a week. So today I'm helping out this morning and then this afternoon I figure I can sit in the library and work on a lecture I'm giving to the medical students later this week (another responsibility of my increasing faculty duties).
I'm sort of sleepy there looking at my laptop screen in the anesthesia library... and I hear "Anesthesia Staff Stat to ER!" This is not normal. This is usually our safety system in the OR, if something crazy is happening in the OR and you need emergency help or an extra hand, anyone can call overhead to get someone into the room. Residents, CRNAs, or even faculty anesthesiologists can call out and get help. i.e. "Anesthesia staff stat to OR 12." So to hear this page at all means something isn't going well. This is the first time I've heard this call to somewhere other than the OR. Usually that is reserved for the Anesthesia group pager or the code Blue pager. So I figure I'd better get off my butt and see if they need a hand. I walk quickly down the hall (I never run, because 1.If I fall on my face they'll be two patients instead of one 2.I'm out of shape ) A couple of other staff are headed the same way. One of them is relatively new and she doesn't even know where the ER is so she joins us. We cruise down the stairs, swipe our IDs through the security door and head toward the trauma bays. Quite a few others are there already in addition to the ER people, some various nurses and other doctors.
I look at the patient and you know they're in trouble. In medical circles it's sometimes referred to as FLK... funny looking kid... A small really tiny kid with small receding jaw with a massive overbite. Almost Pierre-Robin like in look (GIS for Pierre-Robin) I know immediately that he's going to be difficult to intubate. Now as misunderstood as I usually claim anesthesiology is, most would agree that in addition to the ENT surgeons, we are airway specialists. I see them take a look with a laryngoscope and they see nothing. They look with a fiberoptic scope and they see nothing... by now they've called ENT and peds ENT for a possible emergent tracheostomy. Peds anesthesia has been called to bring their code box and airway equipment. Lucky they are barely able to mask ventilate the patient. I also notice the scar on the patient's neck indicating a previous tracheostomy. They're still having no luck with using a fiberoptic scope for intubation. Incidentally someone mentions that this "kid" is 28 years old.... something like 60 pounds and change.
He's starting to breathe now. He had stopped breathing earlier for some still unknown reason. Seizures and sleep apnea are mentioned. Since he's breathing now and still maintaining his oxygen saturation we decide to get up to the OR where more instruments (and a more controlled setting) are available.
So we run up and this patient recieves and awake tracheostomy, which is the ultimate in secure airways. Ends up that this "kid" as an unknown syndrome and some history of autism (though lives on his own) and has been trached in the past for losing his airway during a seizure eight months ago.
This is an anesthesiologist's nightmare. We have all sorts of tricks and techniques to control the airway. But sometimes we fail. The trick is knowing when to call for help as a good senior anesthesiology resident did, and when you've tried things and they aren't working to call for a definitive surgical airway when necessary. It's hard to ask for help. In this case I think we saved this guy's life. Now someone just needs to figure out why he's having seizures (already on two anti-seizure medications)
Saturday, April 09, 2005
Garage?
Taken without permission from an email I received today at work.
Yesterday, a patient remarked as we rolled him into OR 6, "This is the operating room?? It looks like a garage!
Thursday, April 07, 2005
Dedication
I wasn't there Monday. Apparently one of the cardiac surgeons almost passed out during surgery. He said he felt weak and they rushed to get him a chair. He sat down and asked them to call one of his partners down to help until he was feeling better. Evidently they wheeled the patient's transport stretcher in the room and he laid down for a bit. And they used the blood pressure cuff to check his pressure. The other surgeon came down and helped for a bit at which point the surgeon got up, scrubbed again and finished the surgery. I doubt he even went to see his doctor.
Now I don't know if this is all true. I'm hearing it second hand. But i heard it from two people.
(BTW, he's a great surgeon)
Now I don't know if this is all true. I'm hearing it second hand. But i heard it from two people.
(BTW, he's a great surgeon)
Tuesday, April 05, 2005
Rounds
Grand rounds XXVIII is available at Polite Dissent
It's my first submission and post there...
If you're not familiar with term Grand Rounds... it's basically a conference where people talk about a particular subject or recent events in the department. Often there's a guest speaker or something. Evidently it's taken from John Hopkins hospital back in the day. The patient's rooms were in the rotunda and to see them you went "a round" Everything medical has to have "rounds" after it it seems
Seeing patients with your team before the attending arrives is "work rounds"
Seeing patients by yourself before work rounds is "pre-rounding"
Seeing patients with your attending is just "rounds"
Seeing patients with special attending for education purposes is "teaching rounds"
"Grand Rounds" is usually the department's weekly conference.
Eating is "p.o. (per ora) rounds"
Staffing friends
Today I staffed 2 rooms with residents in it. Basically that means being in charge of what happens in both rooms. Also that means I need to try to teach residents. It means that I need to watch them perform procedures that are sometimes tricky. It's very stressful watching someone do something you could do yourself.
Also it it means staffing friends. I've become friends with a lot of the residents because we were in the same program before I was an attending, and we've remained friends. I try to be laid back about the whole process. This morning we bring the patient back into the room after the resident puts in an arterial line and thoracic epidural in the pre-op area. I look at the top of his cart. Now there's supposed to be a bunch of medications available for me to help put the patient asleep. And in addition there's supposed to be some emergency drugs there 'just in case' something happens. I look and there's a couple of syringes of paralytic sitting there. Nothing there to put the patient asleep, nothing to use in case of emergency. He turns and says he forgot the induction agent so we send our medical student running to the pharmacy while we put the patient on monitors. I didn't want to make a big deal of everything so I draw up some emergency drugs while he's fiddling with things. The student comes back and we put the patient asleep. We're getting things worked out and just comment to him that even though we're friends we need to be a little more prepared to do these cases. He gives me a funny look and chuckles. He points to his pocket and the emergency drugs are there ready to go. He says he was wondering why I drew up the other stuff. Ha ha.. now don't I look silly. SO STRESSFUL... people need to tell me things
Also it it means staffing friends. I've become friends with a lot of the residents because we were in the same program before I was an attending, and we've remained friends. I try to be laid back about the whole process. This morning we bring the patient back into the room after the resident puts in an arterial line and thoracic epidural in the pre-op area. I look at the top of his cart. Now there's supposed to be a bunch of medications available for me to help put the patient asleep. And in addition there's supposed to be some emergency drugs there 'just in case' something happens. I look and there's a couple of syringes of paralytic sitting there. Nothing there to put the patient asleep, nothing to use in case of emergency. He turns and says he forgot the induction agent so we send our medical student running to the pharmacy while we put the patient on monitors. I didn't want to make a big deal of everything so I draw up some emergency drugs while he's fiddling with things. The student comes back and we put the patient asleep. We're getting things worked out and just comment to him that even though we're friends we need to be a little more prepared to do these cases. He gives me a funny look and chuckles. He points to his pocket and the emergency drugs are there ready to go. He says he was wondering why I drew up the other stuff. Ha ha.. now don't I look silly. SO STRESSFUL... people need to tell me things
Friday, April 01, 2005
Plane trouble
So guess where i'm supposed to be... Madison. Guess where I'm not... Madison. So I'm on my way to the airport to give some short presentations at a conference in Madison. On the way to the airport I get a call saying my flight is cancelled... So obviously I think it's a prank. So in actuality, my flight is cancelled. In the next 5 minutes I get about 4 calls from people who were also supposed to be on that flight and they have heard the same thing. Apparently there's some sort of crew shortage and we've been rebooked on a flight tomorrow morning after the conference starts. We go to the airport figuring we can work something out there to get to Madison. We get there, to find some very unhelpful staff... I'm on my phone the whole way there trying to get alternative travel arrangements made. Ends up being that the people on the flight have been put on about 6 different flights, mine being one of the later ones. In the midst of trying to get stuff squared away I'm trying to adjust my car rental so I can pick it up in the morning rather than this evening. The man at the car rental place tells me I need to call the website I booked the car with. I call them and they say I need to call the car place. I explain that I've already done that and they assure me that I just need to make another reservation and the other will just go away. Go away? I question this so I don't get a charge on my credit card and she accuses me of not listening. ARGH!!!! At this point i feel like vomitting. This is the first problem i've had with an airline in the past that I can remember. So instead I'll arrive at the conference just before one of my presentations. hopefully the flight in the morning will go well. At least my cat won't be lonely tonight.
Tuesday, March 29, 2005
Eww!
I learned yesterday though a convoluted conversation that there is such a thing as "defecography". Don't ask how we got to it... Don't even ask what it is...
Apparently the "liquid" they use for this test is the consistency of mashed potatoes.
Thank god I'm an anesthesiologist. I'm glad on the other end of the patient.
Defecography is a test used to evaluate the disorders of the lower bowel that are not evident by direct visualization. Radiologic liquid is instilled into the rectum. Then the patient is instructed to empty the rectum while a fluoroscopic exam of the pelvis is carried out. This radiologic test allows the doctor to evaluate the pelvic floor muscles and rectum during defecation. This type of test, although awkward, provides valuable information that will aide your doctor in diagnosing your problem.
The following is a list of conditions for which Defecography can be used to gather more information and/or confirm a diagnosis.
-Rectal prolapse, irritable bowel syndrome, obstructed defecation
-Solitary rectal ulcer, proctalgia, fugax,a rectocele/enterocele
-Fecal incontinence, internal prolapse, constipation
-Rectal/anal intussusception anismus (inappropriate spasm of the anal sphincter)
(UMHS website)
Apparently the "liquid" they use for this test is the consistency of mashed potatoes.
Thank god I'm an anesthesiologist. I'm glad on the other end of the patient.
Sunday, March 27, 2005
Death
I'm watching a documentary filmed at my hospital a few months ago. I've written about it a few times in the past. I've critizized it for being a bit melodramatic and ignoring anesthesiology. That's all okay. Today the showed someone who almost got a liver transplant twice and had it unable to be done for various reasons. Then they showed him dying after having life support withdrawn at somepoint after that. I think they did a great job actually showing that not everything turns out well in the hospital. Not the usual perfect outcome that's usually portrayed. Even though I've seen death in the hospital before it still hits you. Rest in peace.
Supersize Me
Just watched "Supersize Me". As good as people say it is, even though I did doze off a bit in the middle. I can't say it was completely objective or scientific in nature, but it did make a good point. From now on, my Big Mac is eaten with a DIET coke.
(Really I'm just kidding. I haven't drank sugar soda in years.)
(Really I'm just kidding. I haven't drank sugar soda in years.)
Wednesday, March 23, 2005
Extra room
So today I was on cardiac call (as faculty) usually that means you do cardiac cases during the day and then you take over the other cardiac rooms as your cases finish up, then you relieve others and you end up being 3rd from last to leave for the day.
Today was a bit different. The case that was scheduled in our room was cancelled so that a case that had been cancelled because of emergencies, scheduling, etc had been cancelled two days in a row could go. Unfortunately the original surgeon wasn't available so his colleague agreed to do the case for him. The patient wanted her surgeon to do the case, so she didn't want the case done today. So instead of one or two cases as usual, we had none. This you would think is a good thing. It's not. That means ANY case can be put in your room.
The day starts off with a page while I'm driving in that a cardiac case from yesterday needs to come down emergently for bleeding (well he's been bleeding all night) so I take over from the night staff. Usually in cardiac you are staffing one case/one resident at a time. Apparently there's some sort of flu going around (which I think I have, by the way) because two staff anesthesiologists call in sick (which never happens). We end up giving a bunch of clotting factors during the case, plasma, platelets, recombinant factor seven even (something like $5000 a dose) before the guy quits bleeding. As we're finishing up. I get a page. "Would you mind covering another room because we're short staffed?" I say sure no problem figuring they'd give me an easy room because 1) I'm a fairly new faculty and 2) I'm already covering a cardiac case (not a pump case but still) "So we have a ruptured aortic aneurysm coming in and by the way it's a relative of one of our nurse anesthetists" No pressure right? Yikes. If you don't know, a ruptured abdominal aortic aneurysm (AAA) is an anesthesiologist's (and surgeon's) nightmare. Only fifty percent of these patients even reach of the hospital. Another fifty percent of these never leave the OR, a fraction of those leave the hospital (alive that is) Luckily it ends up being a contained rupture of a previous endovascular AAA repair so it's much more stable than you'd think (which is good)
By this time. There are add-on's in my cardiac room. Not cardiac cases, but ENT cases instead followed by a neurosurgery case. bleah. PLUS i'm doing the to-follow vascular case in the other room. That's the breaks. Not bad for a day's work. I did get to leave fairly early for a call day despite the liver transplant added onto the schedule.
Sunday, March 20, 2005
Television
I just saw the side of my head on TV.
Cool eh? I'm famous!
Well not really. The Discovery Channel was at my hospital a few months ago filming stories about residents. I help in part of a heart transplant, so you can see the side of my head over the surgical drapes. Not that I want to be on TV, but they seem to gloss over the anesthesia portion of these cases a lot. Oh well. Surgery makes better television.
Wednesday, March 09, 2005
Trust
Now that I'm more often than before taking the role of an attending anesthesiologist I've decided it's not about your skills, but more about your trust in others. First of all, for those who aren't familiar with the structure of how academic anesthesia works (most private practices I guess also) -- there is an attending anesthesiologist. He/she is "in charge" if the anesthetic. Usually she/he makes the plan and is there for the "critical" potions of the case. In academic anesthesia, usually there is also a resident involved. This is someone who is a licensed doctor, in the midst of her/his training to be a specialist, in this case anesthesia. That person is present for the entire case, and follows the plan of anesthesia set out by the attending. In private practice most places, and some academic centers too, there are also nurse anesthetists. They are nurses that go to special school to perform anesthesia also, usually under the supervision of an attending anesthesiologist. They would perform the same function as a resident -- being present for the entire case and performing the primary anesthetic. (For the rest of this, when I say "resident" I mean "resident or nurse anesthetist") The attending is usually responsible for one to four cases in total depending on the time of day and what type of cases are being performed. Now here are where trust issues come in to play. If the attending was present for the whole case, he/she could perform all the necessary functions and deal with any crises that arise without problem (most of time) because of their previous training. When you are supervising fours rooms, unfortunately you can't be four places at once so you rely on the residents to call you when there are problems. Most of the time, patients receive excellent care from residents -- sometimes even better than if the attending was performing the anesthesia him/herself. Occasionally because of the level of training there is a lapse in judgement, or a delay in calling for help. This is where you can get into trouble. If the resident doesn't call you... and there is a problem still... you are still responsible for the outcome. I trust most of the residents I work with, and I want to give them some space to learn and make their own decisions, but it's hard when i'm responsible for everything they do. So you need to trust their judgement and hope they have a low threshold for notifying you of a problem. I find myself walking from room to room checking things out from the doorway, even though I know everything should be fine. I'm told this nervousness gets better with time. I'm not sure I want it to. A healthy dose of doubt...
why?
Why do doctors talk about work when they meet outside of work. Usually complaining of some sort, or occasionally something freaky or interesting. Maybe it's only residents that do it.
Monday, March 07, 2005
British rotators
Last night was the 2nd annual "Go back to your own country party". It's where we celebrate the leaving of the rotators that come through our department. For some reason, our department has had a history of foreign anesthetists (as they are called at home) come and spend a year or so here as a part of their training. Most are from the UK. Their training is much longer then it is here, so they act as attending anesthesiologists when they arrive here because of their experience. Anyway for the most part they are well trained, relatively young, and very enthusiastic. They are part of the strength of our program in my opinion. It's nice that the department is willing to pay for such a celebration. It's a good boost to morale, especially since it's March already and there's still snow on the ground. Lots of fun was had by all. Even me, though I couldn't drink on the boss's (sp?) dime because I was on call. bleah. Still I had a good time hanging out.
Subscribe to:
Posts (Atom)